See source coverage before you draft.
Project-scoped source management ingests the messy inputs — AE listings, datasets, protocols, PDFs — and turns them into the citable atoms behind every generated section. Writers see source coverage before they draft, so gaps are addressed early, not at QC.
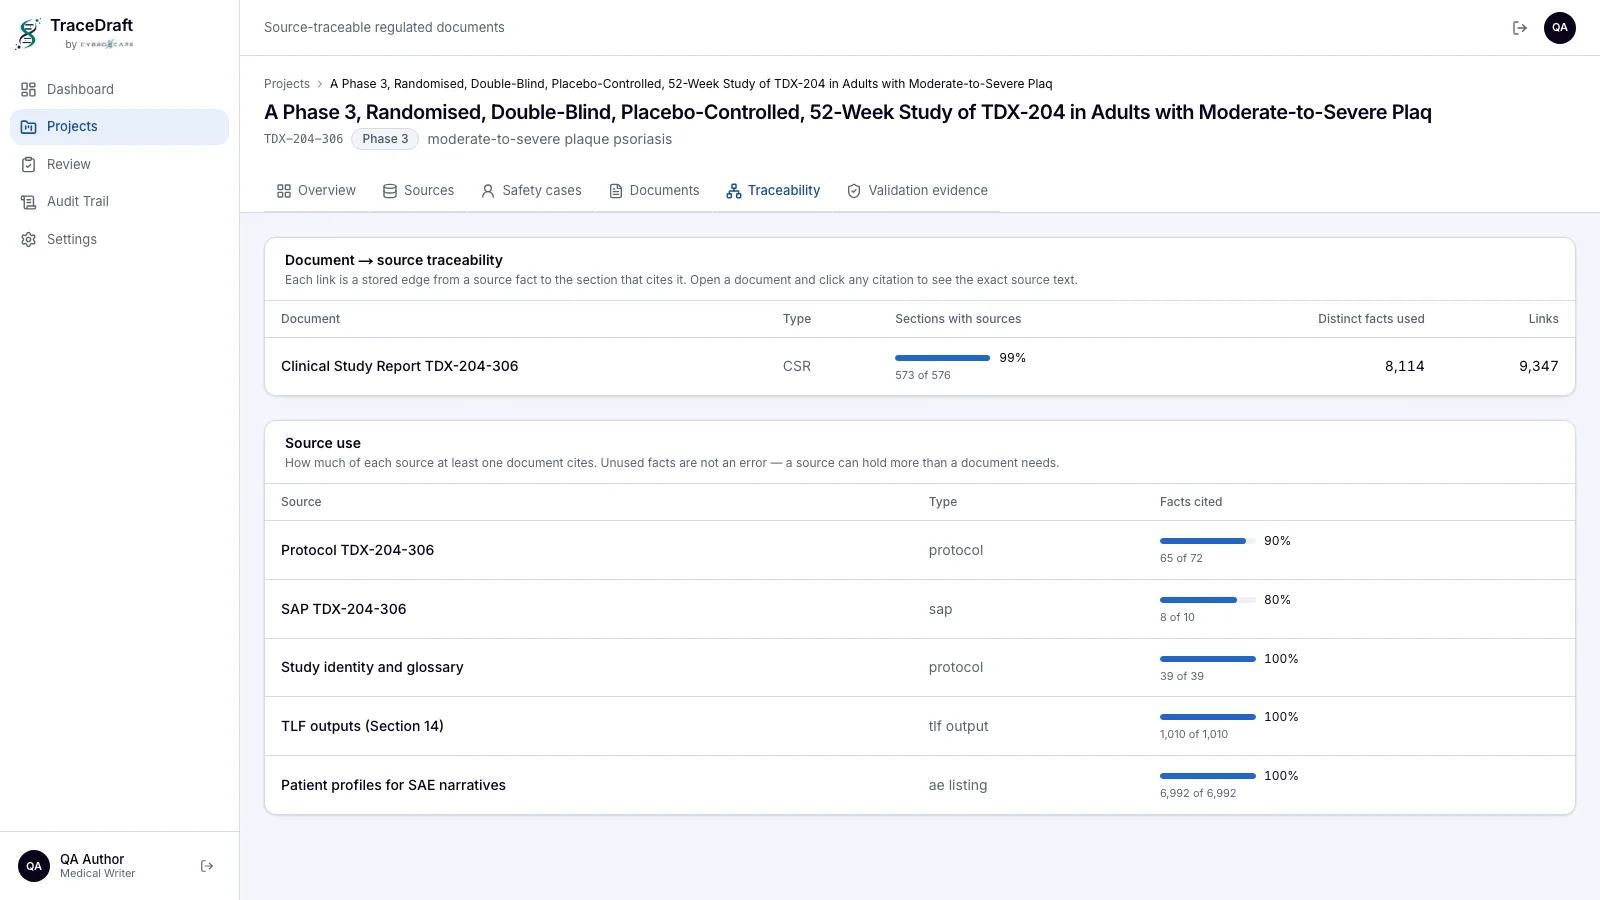
Clinical documentation covers the regulated documents a trial and a submission depend on, such as study reports, safety narratives and CTD summaries. Cybroscape TraceDraft turns your protocols, TLFs, listings and patient profiles into citable source facts, shows which documents each source is ready for, and drafts from them with every sentence cited.
Documents written independently from the same facts
A clinical programme produces dozens of documents that restate the same underlying facts — the same endpoints, the same population definition, the same safety profile, the same study design. Each is written separately, often by different people, often months apart.
The result is a set of documents that disagree with each other in small ways. An endpoint defined slightly differently in the protocol and the statistical analysis plan. A population count in the CSR that does not match the one in the submission summary. A safety statement in the investigator brochure that predates the latest DSUR.
Nobody writes these inconsistencies deliberately. They are what happens when the same fact is retyped twenty times across a programme.
One source of fact per programme
Endpoints, population definitions, study design parameters and abbreviations are defined once and used across documents rather than retyped. When a definition changes, the documents using it are identifiable.
Cross-document consistency stops being a cross-checking exercise performed at the end under time pressure, which is when it is least likely to be done thoroughly.
- 1Adverse event listing · row 14
- 2Lab dataset · ALT value, day 15
- 3Protocol · section 7.2
Provenance that survives export
Links from statement to source persist into the delivered document and its evidence pack, not only inside the authoring tool. A link that disappears on export is useful during writing and worthless during a sponsor audit, which is when the question actually gets asked.
This is the single most useful question to ask any vendor in this category, and it is the one most demos avoid.
A record built for inspection
Generation, review, approval and lock are captured in a hash-chained audit trail that can be verified end to end. A locked document cannot be changed; changes go into a new version.
AI-assisted authoring has to meet the same regulatory bar as human authoring. Anything less and the efficiency is borrowed against a future finding.
What you get
What Clinical Documentation delivers
Clinical Documentation is part of the TraceDraft platform — an AI-native, source-traceable clinical documentation system built for regulated Life Sciences. See how it fits with CSR Authoring, CTD Clinical Summaries, Document Analysis.
- Ingest AE listings, datasets, protocols, PDFs
- Secure source storage
- Fact extraction from source data
- Coverage dashboard for writers
Common questions
Prefer to talk first? Chat with us on WhatsApp or book a call with an expert.
Which clinical documents can be AI-assisted?
Those with substantial data-restatement content: safety narratives, the results sections of study reports and the factual parts of CTD clinical summaries. Interpretation, benefit-risk reasoning and clinical judgement should remain with the writer regardless of how capable the drafting becomes.
Why does provenance need to survive export?
Because the question of where a statement came from is asked during a sponsor audit or a regulatory review, not during authoring. A traceability link that works only inside the vendor's interface is useful while writing and worthless when it matters. Ask any vendor in this category to demonstrate it on an exported document.
How do inconsistencies between clinical documents arise?
From the same fact being retyped across documents written independently, often by different people months apart — an endpoint defined slightly differently in the protocol and the analysis plan, a population count that does not match between the CSR and the submission summary. Sharing defined values rather than retyping them removes the cause.
Related capabilities
All capabilitiesCompose Clinical Study Reports from your linked source data — AE listings, datasets, protocols — and generate the safety narrative appendix straight from the same source graph. One review workflow, one evidence pack, one traceable story from listing to submission.
Learn more about CSR AuthoringCTD Clinical SummariesDraft CTD Module 2.5 Clinical Overviews and Module 2.7 Clinical Summaries from your clinical study reports and integrated analyses. Each section carries the ICH M4E(R2) text it must satisfy, every sentence cites the study report passage or table behind it, and the benefit-risk conclusions stay with your writers.
Learn more about CTD Clinical SummariesDocument AnalysisUpload an existing CSR, a vendor validation protocol, an SOP or a guideline and TraceDraft analyses it against the structure it should follow: a section-by-section summary, what each required section covers, what is missing, and where the text disagrees with itself. Every finding cites the uploaded document.
Learn more about Document AnalysisSafety NarrativesA standard safety narrative template — Patient Identification, AE Description, Medical History, Study Drug, Clinical Course, Causality and Narrative Summary — with each section wired to the source types it needs. The final narrative slots directly into the CSR appendix.
Learn more about Safety NarrativesHuman-in-the-Loop ReviewsA dedicated review queue routes generated sections to human reviewers with the source-link count in view — so reviewers validate AI output against the actual data behind it. The section status workflow keeps everyone honest about where a draft actually is.
Learn more about Human-in-the-Loop ReviewsClinical AutomationGeneration, extraction and export run asynchronously so writers never wait for a spinner. Combined with the swappable AI provider, teams can automate draft production while keeping the human review gate exactly where it belongs.
Learn more about Clinical AutomationSee clinical documentation on your own data.
Bring a protocol, a TLF set or an AE listing. We show you a source-traced draft built from it.
- We reply within one business day
- We run your inputs live on the call
- You see every sentence linked to its source